
Whistleblower Medicaid Fraud Attorneys
Medicaid plays a critical role in providing healthcare services to eligible low-income adults, children, pregnant women, seniors, and people with disabilities. Funded jointly by the federal government and states, Medicaid’s extensive reach and substantial budget necessitate vigilant oversight to prevent and address fraud and abuse. The complexity and scale of Medicaid, involving significant expenditures, underscore the importance of whistleblower involvement in identifying fraudulent activities.
The Medicaid fraud lawyers at Di Pietro Partners represent whistleblowers. We understand the courage it takes to step forward and the importance of ensuring your rights and interests are protected throughout the process. Our attorneys handle eligible False Claims Act whistleblower matters on a contingency-fee basis. For qualifying cases, attorney fees are generally contingent upon obtaining a recovery, subject to the terms of the firm’s written fee agreement.
If you suspect Medicaid fraud and are considering taking action, contact Di Pietro Partners for a confidential consultation.
Our Medicaid Fraud Lawyers on TV
What is Medicaid Fraud/Abuse?
Medicaid fraud generally involves an intentional deception or misrepresentation made with knowledge that it could result in an unauthorized benefit. Medicaid abuse is different. It can include provider practices that are inconsistent with sound fiscal, business, or medical practices and result in unnecessary Medicaid costs, reimbursement for medically unnecessary services, or services that do not meet professionally recognized standards of care. Whether particular conduct constitutes fraud or abuse depends on the specific facts, including the person’s knowledge and intent.
Medicaid’s mission is to deliver necessary healthcare services to eligible individuals and families, managing substantial financial allocations annually. The program’s expansive scope and complexity make vigilant oversight essential to prevent fraud and abuse, with healthcare workers, patients, industry insiders, and other whistleblowers playing an important role in identifying suspicious practices.
Medicaid fraud is a form of healthcare fraud and may involve knowingly submitting or causing false or fraudulent claims for payment.. Common manifestations of Medicaid fraud include:
Billing for Services Not Rendered: Healthcare providers may knowingly submit claims for procedures or services that were never administered to the patient. For example, a clinic might charge Medicaid for advanced diagnostic tests that were never actually conducted.
Upcoding: Providers may knowingly use billing codes representing more expensive or complex services than were actually performed or supported by the medical record in order to obtain higher Medicaid reimbursement.
Unnecessary Procedures: Knowingly billing Medicaid for medically unnecessary services may constitute fraud when the applicable legal requirements are met. An unnecessary service does not automatically establish fraud; the circumstances, including knowledge and intent, matter.
False Documentation: Fraud may involve creating or altering records to support false Medicaid claims, including documentation for procedures that were never performed, patients who were never treated, or home health services that never occurred.
The diligent identification and rectification of Medicaid fraud and abuse are vital for maintaining the integrity of the program. Whistleblowers are supported by legal frameworks and protections to report suspected misconduct, helping ensure Medicaid resources rightly aid those requiring medical services.
Who Can Be a Medicaid Whistleblower?
Medicaid fraud is often discovered by people who work inside healthcare organizations and see billing, treatment, documentation, reimbursement, or operational practices firsthand. Under the False Claims Act, an eligible private person may bring a qui tam action on behalf of the United States, although statutory restrictions and other legal requirements can affect whether a particular person or claim qualifies.
Potential Medicaid whistleblowers may include:
- Medical billers and coders
- Physicians and medical directors
- Nurses and nurse practitioners
- Physician assistants and medical assistants
- Compliance officers
- Revenue cycle and reimbursement personnel
- Hospital and health system employees
- Skilled nursing facility employees
- Home health and hospice employees
- Medicaid managed-care organization employees
- Pharmacy and laboratory employees
- Durable medical equipment company employees
- Behavioral health and mental health facility employees
- Practice administrators and healthcare executives
- Contractors, consultants, and third-party vendors
A whistleblower does not necessarily need to be a physician, executive, or compliance officer. Employees who understand how Medicaid claims are coded, documented, approved, submitted, or reimbursed may be especially well positioned to recognize patterns that outsiders would not see.
Not everyone with information about suspected Medicaid fraud is automatically entitled to file a qui tam case or receive a whistleblower award. Eligibility can depend on the specific facts and the requirements of the False Claims Act and other applicable law.
How to Report Medicaid Fraud
Reporting Medicaid fraud is essential for maintaining the integrity of healthcare services and ensuring that resources are distributed fairly. If you suspect fraudulent activities within the Medicaid system, it is important to take the following steps:
- Collect or Identify Relevant Information – Begin by gathering or identifying information related to the suspected fraud. This may include billing records, communications, internal reports, or other documents that could support your concerns. However, potential whistleblowers should be careful when accessing, copying, or removing employer records. Documents may contain confidential, privileged, or protected health information, and whether particular records may lawfully be obtained or retained depends on the circumstances. Consider speaking with an attorney before taking documents that are not already lawfully in your possession.
- Document Your Observations – Promptly write a detailed account of your observations and the specifics of the suspected fraud. Considering that investigations and legal processes may take years to conclude, this documentation can serve as an important record, preserving the accuracy of your recollections. Include relevant dates, individuals involved, billing practices, claim information, and how you became aware of the suspected conduct when possible.
- List Additional Relevant Documents – Identify any documents that could be related to your case but are not currently in your possession. This might encompass internal records, billing details, or known correspondence that you cannot directly access. Such a list will aid investigators and legal advisors in their efforts to thoroughly examine the case.
- Consult a Medicaid Fraud Lawyer – Seek the advice of an attorney experienced in Medicaid fraud and False Claims Act matters. An attorney can evaluate whether the allegations may support a qui tam action or another type of government report and explain the procedures, deadlines, confidentiality considerations, and whistleblower protections that may apply.
- Report to Government Agencies – Suspected Medicaid fraud may be reported to the U.S. Department of Health and Human Services Office of Inspector General (HHS-OIG). Depending on the conduct and state involved, reports may also be made to the appropriate state Medicaid agency or Medicaid Fraud Control Unit (MFCU). HHS-OIG accepts complaints involving false Medicaid claims, kickbacks, and other fraud, waste, or abuse involving HHS programs
Reporting suspected Medicaid fraud to an agency is not the same as filing a False Claims Act qui tam lawsuit. A qui tam action follows a separate federal court process. The complaint is initially filed under seal, and the relator must provide the government with a written disclosure of substantially all material evidence and information possessed.
Consider Whistleblower Protections – If you’re exposing suspected fraud within your organization, be aware of the whistleblower protections provided by federal and, in some circumstances, state law. The federal False Claims Act contains an anti-retaliation provision protecting certain employees, contractors, and agents who engage in protected conduct. The protections available depend on the particular facts and applicable law.
By following these steps, you can contribute to efforts to identify Medicaid fraud while protecting the integrity of your information and legal rights. Because reporting routes and whistleblower rights can differ depending on the circumstances, potential whistleblowers may benefit from legal advice before deciding how to proceed.
Medicaid Fraud Whistleblower Rewards
Whistleblowers play a vital role in exposing Medicaid fraud. Under the federal False Claims Act, eligible private individuals with knowledge of fraud against the government may file a qui tam lawsuit on behalf of the United States.
It is vital to use an experienced Medicaid fraud attorney to file this type of lawsuit. An individual who files a qui tam lawsuit is known as a relator.
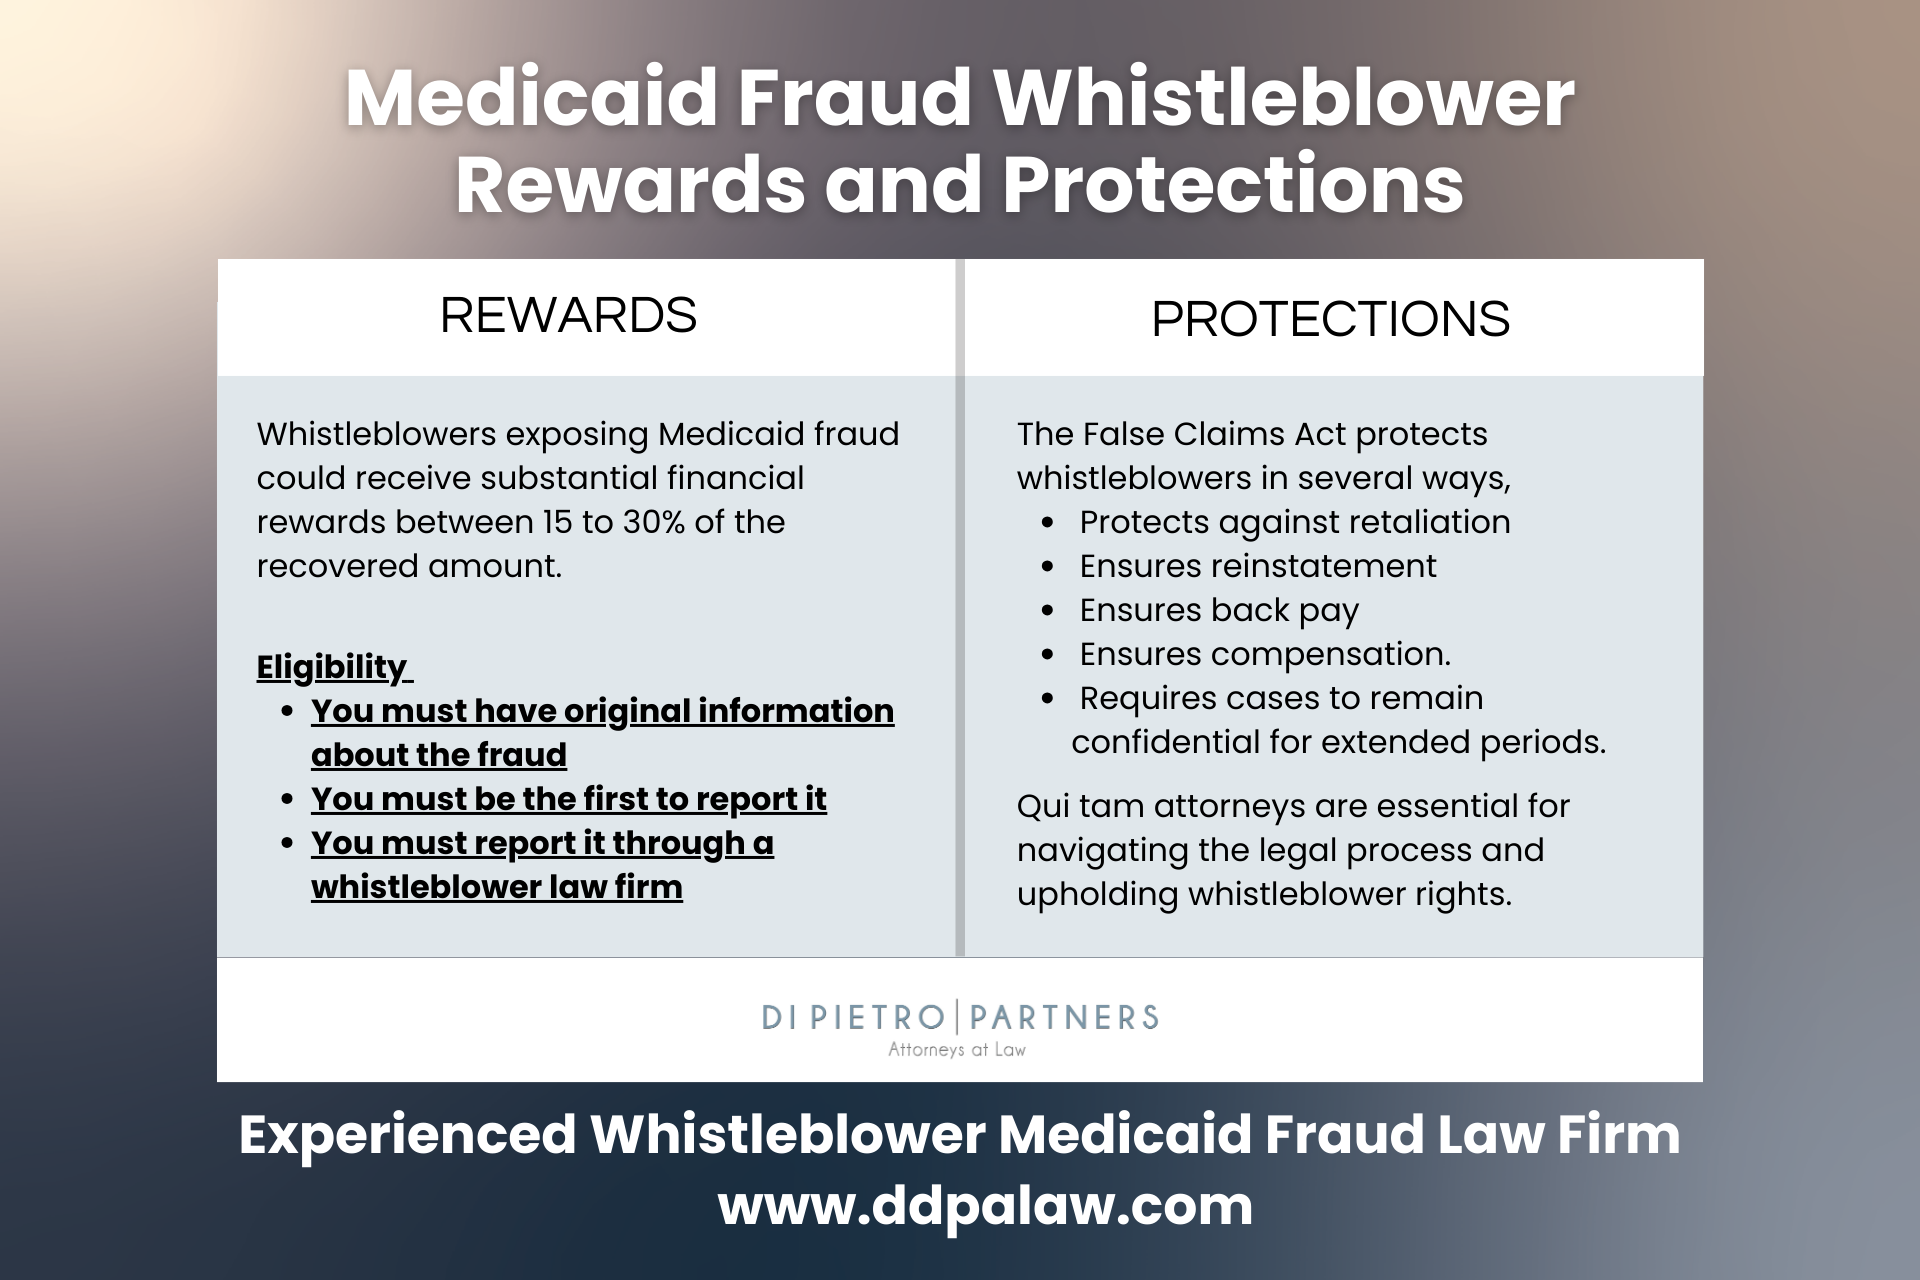
If the government intervenes and proceeds with the case, a successful relator generally receives between 15% and 25% of the proceeds recovered through the lawsuit or settlement. If the government declines to intervene and the relator successfully pursues the case, the relator generally receives between 25% and 30% of the recovery. These percentages are subject to statutory exceptions and may be reduced in certain circumstances.
Of course, another point to consider is how do you know this illegal activity is happening? Has your employer forced you to be involved in any way? Considering these questions, if you know that Medicaid fraud may be occurring where you work, contact a Medicaid fraud attorney to discuss whether the information may support a False Claims Act case or another type of report.
Medicaid Whistleblower Retaliation Protections
The False Claims Act protects certain employees, contractors, and agents from retaliation because of lawful acts taken in furtherance of a False Claims Act case or other lawful efforts to stop suspected violations of the Act.
Retaliation can include being:
- Fired
- Demoted
- Suspended
- Threatened
- Harassed
- Otherwise discriminated against in the terms and conditions of employment because of protected whistleblower activity
Under 31 U.S.C. § 3730(h), qualifying individuals may be entitled to relief intended to make them whole, including:
- Reinstatement with the same seniority status
- Two times the amount of back pay
- Interest on back pay
- Compensation for certain special damages
- Litigation costs
- Reasonable attorneys’ fees
A False Claims Act retaliation claim generally must be brought within three years of the retaliatory act.
Not every workplace dispute or adverse employment action qualifies as unlawful retaliation. Whether the False Claims Act protects a particular employee, contractor, or agent depends on the conduct involved, the employer’s actions, and the connection between the protected activity and the retaliation. State whistleblower laws may provide additional protections in some Medicaid matters.
Healthcare workers who believe they are being punished for raising concerns about Medicaid fraud should consider speaking with an attorney promptly about their rights and applicable deadlines.
Recent Medicaid Fraud Cases
Medicaid fraud investigations and False Claims Act cases continue to produce substantial recoveries nationwide. In fiscal year 2025, Medicaid Fraud Control Units reported nearly $2 billion in combined criminal and civil recoveries, 1,185 convictions, and 674 civil settlements and judgments.
Recent Medicaid fraud and whistleblower matters include:
Kentucky Medicaid False Claims Settlements (2026) – Six defendants agreed to civil settlements totaling approximately $23.8 million to resolve allegations involving false Medicaid claims for services that were not provided or were affected by improper financial conflicts of interest. The matter originated from a qui tam lawsuit filed by a private whistleblower.
PA Lifesharing Medicaid Case (2026) – PA Lifesharing agreed to pay approximately $1.21 million to resolve allegations that it billed Medicaid for services provided by direct-support professionals who were not properly cleared or trained. The case was filed under the False Claims Act’s qui tam provisions, and the whistleblower received approximately $242,219
CVS Medi-Cal Settlement (2025) – CVS Pharmacy paid approximately $18.2 million to resolve allegations that it knowingly submitted claims to California’s Medicaid program, Medi-Cal, for certain prescriptions that did not satisfy applicable diagnosis and documentation requirements. The case was brought by a former CVS pharmacist under the False Claims Act, and the whistleblower received approximately $3.3 million
Safire Nursing Facilities Medicaid Case (2026) – Three nursing facilities agreed to pay $9 million to resolve allegations involving false claims submitted to Medicare and Medicaid for rehabilitation therapy that was allegedly medically unnecessary, unsupported by records, improperly documented, or not provided. The case originated from a qui tam whistleblower action.
These examples illustrate the range of conduct that may lead to Medicaid fraud enforcement, including billing for services not provided, medically unnecessary services, deficient documentation, unqualified personnel, and other false claims. Settlements involving unresolved allegations generally do not constitute admissions or findings of liability.
How Our Medicaid Whistleblower Attorneys Can Help
Our Medicaid fraud attorneys play a pivotal role in supporting whistleblowers to expose fraudulent practices within the healthcare system.
We start by conducting a thorough evaluation of the alleged fraud, applying our deep knowledge of healthcare law to assess the feasibility of initiating a whistleblower (qui tam) case under the False Claims Act. This initial review is crucial for ensuring the case is robust and fulfills the criteria necessary for whistleblower actions.
Following the decision to move forward, our attorneys guide whistleblowers through the process of preparing and filing a qui tam lawsuit. This includes preparing the complaint and a written disclosure of substantially all material evidence and information the whistleblower possesses for the government. The complaint is initially filed under seal and is not served on the defendant until the court orders otherwise.
During the seal period, the government investigates the allegations and decides whether to intervene and take primary responsibility for the case or decline intervention. If the government declines, the whistleblower may have the right to continue pursuing the action.
Our attorneys can represent and advise whistleblowers throughout this process, communicate with government attorneys and investigators when appropriate, and protect the whistleblower’s interests as the case develops.
Why Medicaid Whistleblowers Choose Di Pietro Partners
Healthcare Fraud Experience From Multiple Perspectives
Di Pietro Partners represents whistleblowers in False Claims Act matters as well as healthcare providers in separate regulatory and litigation matters. This experience gives the firm insight into both the allegations raised by Medicaid fraud whistleblowers and the billing practices, documentation, medical-necessity issues, compliance requirements, and defenses that may become important as a case develops.
Firsthand Experience as a False Claims Act Relator
David Di Pietro also has firsthand experience with the whistleblower process. He previously served as a False Claims Act relator in a qui tam action involving 21st Century Oncology and Broward Health. That experience gives him a perspective few attorneys can claim: he has personally experienced what it means to step forward as a relator and participate in the federal qui tam process.
More Than 20 Years of Litigation and Trial Experience
Medicaid False Claims Act cases can involve complex questions of healthcare billing, federal and state reimbursement requirements, medical necessity, and government investigations. David has more than 20 years of litigation experience, has tried more than 70 jury trials, and has handled hundreds of bench trials and evidentiary hearings. His practice includes healthcare law, healthcare litigation, and whistleblower and qui tam matters.
Healthcare Leadership Experience
David previously served as Chairman of the North Broward Hospital District, commonly known as Broward Health. That leadership experience provided firsthand exposure to the operations and governance of a major public healthcare system, including healthcare compliance, physician relationships, reimbursement issues, risk management, and institutional decision-making.
Federal Government and Qui Tam Experience
The firm’s team includes a former U.S. Department of Justice attorney, adding federal-government experience to matters that may involve DOJ, U.S. Attorney’s Offices, HHS-OIG, state Medicaid agencies, Medicaid Fraud Control Units, and other government authorities.
Medical Insight Within the Firm
Many Medicaid fraud cases turn on medical questions: Was a service medically necessary? Does the documentation support the diagnosis or level of care? Does the treatment described in the medical record match what was billed to Medicaid?
Dr. Tiffany Di Pietro serves as Medical Advisor to Di Pietro Partners. She is a licensed Florida physician and quadruple board-certified in Internal Medicine, Cardiology, Echocardiography, and Nuclear Cardiology. Her clinical background can provide the legal team with additional medical insight when evaluating medical records, diagnoses, treatment patterns, and medical-necessity issues in appropriate cases.
Nationwide Medicaid Whistleblower Representation
Although Medicaid programs are administered at the state level under federal requirements, Medicaid fraud can implicate federal False Claims Act liability and other federal and state laws. Di Pietro Partners evaluates qualifying Medicaid whistleblower matters nationwide, including allegations involving false billing, medically unnecessary services, managed-care fraud, home health and nursing facility services, durable medical equipment, prescription drugs, kickbacks, and other suspected false claims.
Contingency-Fee Representation for Eligible Cases
Di Pietro Partners handles eligible False Claims Act whistleblower matters on a contingency-fee basis. For qualifying cases, attorney fees are generally contingent upon obtaining a recovery, subject to the terms of the firm’s written fee agreement.
Types of Medicaid Fraud

Billing for Services Not Rendered: A typical example could involve a mental health clinic that only provides basic counseling sessions but submits Medicaid claims for comprehensive psychiatric evaluations and therapeutic procedures that never occurred. Knowingly billing Medicaid for services that were never actually provided may constitute fraud.
Upcoding: Healthcare providers may deliberately use billing codes for more complex or expensive services than those actually delivered or supported by the medical record in order to obtain higher reimbursement.
Unnecessary Procedures: Knowingly billing Medicaid for medically unnecessary services or procedures may constitute fraud when the applicable legal requirements are met. An unnecessary or improper service does not automatically establish fraud; the provider’s knowledge and intent are important.
False Documentation: Fraud may involve creating, altering, or falsifying records to support Medicaid claims, including records for services that were never provided, patients who were never treated, or home health visits that never occurred.
Kickbacks and Referrals: This can involve knowingly and willfully offering, paying, soliciting, or receiving remuneration to induce or reward referrals, purchases, orders, or recommendations involving items or services payable by Medicaid or another federal healthcare program. Certain arrangements may qualify for statutory exceptions or regulatory safe harbors.
Phantom Billing: This generally involves billing Medicaid for services, procedures, supplies, or equipment that were never actually provided to the beneficiary. Billing for a more expensive service than was provided is generally considered upcoding, while knowingly billing multiple times for the same service may involve duplicate billing.
Upcoding of Patient Diagnosis: This can involve knowingly submitting unsupported or exaggerated diagnosis information when that information affects Medicaid reimbursement, eligibility for particular services, or payments under a Medicaid managed-care arrangement.
Prescription Fraud: Medicaid prescription-drug fraud may include billing for drugs that were never dispensed, submitting false prescription claims, diverting prescription medications, or using kickbacks or other fraudulent arrangements to generate Medicaid-reimbursed prescriptions.
Identity Theft: Fraud may involve improperly using a Medicaid beneficiary’s information or a healthcare provider’s billing credentials to obtain services or submit claims for services that were never provided.
Equipment Fraud: Durable medical equipment fraud may involve knowingly billing Medicaid for equipment or supplies that were never delivered, were not ordered as represented, or were not medically necessary.
Medicaid Fraud Red Flags Healthcare Employees May Notice
Healthcare employees are often in a unique position to recognize billing, documentation, treatment, or reimbursement patterns that may not be visible to patients or outside investigators. A single unusual claim does not necessarily establish fraud, but repeated patterns or instructions that appear designed to obtain improper Medicaid payments can be warning signs.
Potential red flags may include:
- Billing Medicaid for services, procedures, supplies, or equipment that employees know were never actually provided.
- Pressure to use higher-paying billing codes that are not supported by the services performed or the medical record.
- Repeated billing for services that appear medically unnecessary or unsupported by the patient’s condition.
- Medical records being altered, backdated, or created after the fact to support claims that have already been submitted.
- Claims being submitted under the name or credentials of a provider who did not perform or supervise the service as represented.
- Services being billed as though they were provided by qualified personnel when employees know the individuals performing them were unqualified, improperly supervised, excluded from federal healthcare programs, or otherwise ineligible.
- Bonuses, commissions, referral payments, or other financial incentives tied to Medicaid-reimbursed referrals, prescriptions, services, transportation, equipment, or patient volume when those arrangements may improperly influence healthcare decisions.
- Patients being billed for services or equipment they did not receive, request, or need.
- Duplicate claims or repeated billing for the same service without an apparent legitimate reason.
- Billing practices that do not match what physicians, nurses, therapists, billers, coders, or other employees actually observe occurring in the workplace.
- Pressure on employees to participate in, approve, or conceal questionable Medicaid billing practices.
- Patterns involving Medicaid managed-care claims, encounter data, provider information, or reimbursement that appear inconsistent with the care actually provided.
These warning signs do not automatically mean Medicaid fraud has occurred. Whether conduct violates the False Claims Act or another healthcare fraud law depends on the specific facts, including what was billed, what Medicaid required, and what the people involved knew or intended. Employees who repeatedly encounter suspicious practices may want to document what they observed and speak with a Medicaid fraud attorney before taking further action.
Federal Medicaid Fraud Laws
Federal Medicaid fraud laws serve to safeguard the Medicaid program’s integrity by imposing penalties on fraudulent activities designed to manipulate or misappropriate federal and state healthcare funds. These regulations span a broad spectrum of statutes, targeting different forms of fraud and misconduct within the Medicaid system. Below is a summary of significant federal laws pertaining to Medicaid fraud:
False Claims Act (FCA): The FCA prohibits knowingly presenting, or causing to be presented, false or fraudulent claims for payment or approval by the federal government. Liability may also arise from knowingly using false records or statements material to false claims and from other conduct covered by the statute. The FCA also contains qui tam provisions allowing eligible private individuals to bring lawsuits on behalf of the United States and potentially receive a share of a successful recovery.
Anti-Kickback Statute (AKS): The AKS makes it a criminal offense to knowingly and willfully offer, pay, solicit, or receive remuneration to induce or reward referrals or generate business involving items or services payable by a federal healthcare program, including Medicaid. Certain arrangements may qualify for statutory exceptions or regulatory safe harbors.
Physician Self-Referral Law (Stark Law): The Stark Law generally prohibits physicians from referring Medicare patients for certain designated health services to an entity with which the physician or an immediate family member has a financial relationship, unless an exception applies. Section 1903(s) of the Social Security Act extends the referral prohibition to Medicaid.
Health Care Fraud Statute: This statute criminalizes the knowing and willful execution, or attempted execution, of a scheme to defraud a healthcare benefit program or obtain money or property from such a program through false or fraudulent pretenses, representations, or promises in connection with healthcare benefits, items, or services.
Violations of these laws can result in severe penalties, including fines, restitution, civil liability, exclusion from federal healthcare programs, and imprisonment when criminal statutes apply. The federal government, through agencies such as the Department of Health and Human Services Office of Inspector General (HHS-OIG) and the Department of Justice (DOJ), investigates and enforces healthcare fraud laws and works to recover improperly obtained government funds.
Medicaid Drug Rebate Program
Medicaid agencies, and participating drug manufacturers that helps offset the federal and state costs of most outpatient prescription drugs provided to Medicaid beneficiaries. Drug manufacturers generally must enter into a National Drug Rebate Agreement with HHS in order for states to receive federal Medicaid funding for most of the manufacturer’s covered outpatient drugs.
The program requires manufacturers to report pricing information to CMS, including the Average Manufacturer Price (AMP) and other required drug-pricing data. CMS uses manufacturer-reported pricing information to calculate or provide states with the Unit Rebate Amount (URA), although manufacturers remain responsible for correctly calculating the applicable rebate.
For single-source and innovator multiple-source drugs, the basic rebate is generally the greater of 23.1% of AMP or the difference between AMP and the drug’s best price, with additional inflation-based rebate requirements potentially applying.
For non-innovator multiple-source drugs, which generally include generic drugs, the basic rebate is 13% of AMP. Since 2017, these drugs may also be subject to an additional inflation-based rebate.
False or inaccurate drug-pricing information can have significant consequences because reported pricing affects the rebates manufacturers owe Medicaid. Depending on the facts and applicable legal requirements, knowingly providing false pricing information or otherwise improperly reducing Medicaid rebate obligations may lead to government enforcement or False Claims Act allegations.
Our Medicaid fraud lawyers evaluate whistleblower matters involving suspected manipulation of Medicaid drug pricing, rebate obligations, and other conduct that may improperly reduce amounts owed to Medicaid. For individuals with firsthand knowledge of suspected misconduct involving the Medicaid Drug Rebate Program, we offer confidential case evaluations to discuss whether the information may support a False Claims Act claim or another government report.
Other Types of Healthcare Fraud
Besides Medicaid fraud, the healthcare industry faces various other types of fraud that can significantly impact both the financial integrity of healthcare systems and patient care. These include:
Medicare Fraud – Medicare fraud encompasses knowingly or intentionally using false claims, representations, documentation, or other deceptive conduct to improperly obtain Medicare payments. Medicare provides coverage primarily to individuals age 65 and older, as well as certain younger people with disabilities, End-Stage Renal Disease, or ALS. Potential Medicare fraud may include billing for services not provided, upcoding, false documentation, kickbacks, and knowingly billing for medically unnecessary services.
Private Insurance Fraud – This type of fraud involves knowingly submitting false or fraudulent claims to private health insurance companies. Tactics may include billing for services not provided, improper duplicate billing, falsifying records, and performing or billing for unnecessary procedures as part of a fraudulent scheme.
Prescription Drug Fraud – Prescription drug fraud can involve various schemes, including billing for prescriptions that were never dispensed, falsifying prescription information, diversion or unlawful distribution of medications, and kickback arrangements. Pharmaceutical-company conduct may also lead to False Claims Act liability when it knowingly causes false or non-covered claims to be submitted to Medicaid or other government healthcare programs. DOJ cases have involved off-label promotion where the alleged conduct caused non-covered claims to be submitted, rather than treating off-label prescribing itself as automatically fraudulent.
Kickbacks and Referral Schemes – Illegal kickbacks may involve knowingly and willfully offering, paying, soliciting, or receiving remuneration to induce or reward referrals, purchases, orders, or recommendations involving items or services payable by a federal healthcare program. Certain arrangements may qualify for statutory exceptions or regulatory safe harbors.
Provider Identity Theft – Fraudsters may use a healthcare provider’s identity or billing credentials to submit false claims for services never rendered or facilitate other fraudulent billing schemes.
Upcoding and Unbundling – Upcoding involves billing for a more expensive service than was actually provided or supported by the documentation, while unbundling refers to improperly billing separately for services that should be billed together under an applicable coding or payment rule. When performed knowingly to obtain improper reimbursement, these practices may constitute healthcare fraud. CMS identifies upcoding and unbundling as practices that can fall within fraud or abuse depending on the facts, intent, and knowledge.
False or Exaggerated Claims for Disability Benefits – Knowingly making false statements or concealing material information to obtain or continue receiving disability benefits may constitute fraud. This can include misrepresenting one’s health condition, employment status, or income.
Addressing these types of healthcare fraud requires vigilant monitoring, strict enforcement of laws, and public awareness. Healthcare fraud not only drains resources but also compromises patient care and increases costs for everyone in the healthcare system.
Medicaid Fraud FAQ
Q. How Long Do You Have to File a Medicaid False Claims Act Case?
The False Claims Act contains its own statute of limitations. In general, an FCA action may not be brought more than six years after the alleged violation, or more than three years after the material facts were known or reasonably should have been known by the responsible U.S. government official, whichever period ends later. However, an action generally cannot be brought more than 10 years after the alleged violation. U.S. Code
Because the applicable deadline can depend on when the conduct occurred and when the government learned of the material facts, potential Medicaid whistleblowers should not assume they have the full 10 years to act. Anyone considering a qui tam case should speak with an attorney as early as possible so the relevant deadlines can be evaluated.
Q. What happens when you report medicaid fraud?
Once you report Medicaid fraud, the relevant agency reviews the information to determine what action, if any, is appropriate. Not every report results in an investigation, and the agency may contact the person who submitted the report if additional information is needed. HHS-OIG specifically notes that it receives thousands of complaints and cannot investigate or respond individually to every submission.
Depending on the circumstances, suspected Medicaid fraud may lead to civil enforcement, administrative action, recovery of improperly paid funds, exclusion from federal healthcare programs, or criminal prosecution.
A False Claims Act qui tam lawsuit follows a different process. The lawsuit is initially filed under seal while the government investigates the allegations and decides whether to intervene.
Q. Where do you report medicaid fraud?
Medicaid fraud may be reported to the U.S. Department of Health and Human Services Office of Inspector General (HHS-OIG). Depending on the state and nature of the suspected conduct, reports may also be made to the state Medicaid agency or the state’s Medicaid Fraud Control Unit (MFCU). HHS-OIG oversees state MFCUs, which investigate and prosecute Medicaid provider fraud and patient abuse or neglect.
Individuals considering a False Claims Act whistleblower case should understand that filing a qui tam lawsuit is different from simply submitting a fraud report to a government agency. Consulting with a Medicaid fraud attorney can help determine which route may be appropriate.
Q. How do you report medicaid fraud anonymously?
HHS-OIG allows individuals to submit fraud complaints anonymously without providing identifying information. A person may also identify themselves to HHS-OIG while requesting confidentiality. However, HHS-OIG warns that remaining anonymous may limit its ability to thoroughly review or resolve a complaint.
An anonymous agency complaint is different from filing a False Claims Act qui tam lawsuit. Attorney-client privilege protects qualifying confidential communications between an attorney and client, but hiring an attorney does not by itself make a qui tam relator anonymous to the government or court. Individuals considering a qui tam action should obtain legal advice before deciding how to report the suspected fraud.
Q. How long does a medicaid fraud investigation take?
The duration of a Medicaid fraud investigation can vary significantly depending on the complexity of the allegations, the amount of evidence involved, the number of individuals or entities under investigation, and the agencies involved.
There is no standard investigation timeline, and potential whistleblowers should not assume that a Medicaid fraud investigation will conclude within a particular number of months or years. False Claims Act matters may also involve a separate sealed investigation period while the government determines whether to intervene.
Q. What is the cost of a Medicaid fraud lawyer?
The cost of hiring a Medicaid fraud lawyer can vary based on the attorney, law firm, and type of matter. Di Pietro Partners handles eligible False Claims Act whistleblower cases on a contingency-fee basis. For qualifying cases, attorney fees are generally contingent upon obtaining a recovery, subject to the terms of the firm’s written fee agreement. This means qualifying whistleblowers generally do not pay hourly attorney fees as the case progresses.
Talk to a Medicaid Fraud Attorney
Given the complexities and potential consequences of reporting Medicaid fraud, consulting with a specialized Medicaid fraud attorney can be an important step. Whether you’re a healthcare professional who’s noticed questionable billing practices or another insider with firsthand knowledge of suspected fraud, your information can play a pivotal role in safeguarding the integrity of Medicaid and protecting vital resources.
At Di Pietro Partners, our team of Medicaid fraud attorneys brings together healthcare law experience, more than 20 years of litigation experience, former federal government experience, public healthcare leadership, and physician-level medical insight. David Di Pietro has also personally served as a False Claims Act relator, giving him firsthand experience with the federal qui tam process from the whistleblower’s perspective.
Dr. Tiffany Di Pietro, a licensed Florida physician who is quadruple board-certified in Internal Medicine, Cardiology, Echocardiography, and Nuclear Cardiology, serves as the firm’s Medical Advisor. Her clinical background can provide additional insight in Medicaid fraud matters involving medical necessity, diagnosis coding, treatment documentation, and other complex medical issues.
We understand the courage it takes to step forward and the importance of ensuring your rights and interests are protected throughout the process. That’s why we offer a confidential, no-obligation consultation to discuss your case and explore your legal options. Di Pietro Partners handles eligible Medicaid False Claims Act whistleblower matters on a contingency-fee basis. For qualifying cases, attorney fees are generally contingent upon obtaining a recovery, subject to the terms of the firm’s written fee agreement.
If you suspect Medicaid fraud and are considering taking action, don’t navigate this challenging landscape alone. Contact Di Pietro Partners to confidentially discuss what you know, whether the conduct may support a False Claims Act claim, and the options available for reporting suspected Medicaid fraud.

